Sports Knee Injuries Abroad: Meniscus and Cartilage Surgery Questions
Meniscus and cartilage surgery abroad: what imaging shows, repair versus removal, cartilage procedures, assessment standards and realistic recovery timelines.
Knee injuries in active people rarely arrive with a clean label. A twisting fall on a football pitch, a sudden stop on a tennis court, or a ski edge that catches too early can produce a meniscus tear, a cartilage defect, a ligament sprain or some combination of all three, and the symptoms overlap far more than patients expect. By the time someone starts looking at treatment abroad, they have usually had an examination, possibly a scan, and a recommendation they are not entirely sure about.
This guide is about the questions worth asking when surgery for meniscus or cartilage damage is on the table in another country. It covers what the imaging can and cannot show, why the same scan can produce different plans in different clinics, what meniscus repair and meniscectomy mean for a knee over twenty years, and how to judge whether a clinic is treating your knee or its own surgical volume.
Aurevon Health is an intermediary and not a medical provider. Nothing here is clinical advice or a recommendation for your case; it is preparation for a more useful conversation with the professionals who will assess you.
Why the diagnosis is less obvious than it looks
Meniscal tears are the most commonly operated knee injury in Europe, and they are also one of the most commonly over treated. Imaging studies in people without knee pain regularly find meniscal tears, particularly in those over forty, which means the presence of a tear on a scan does not by itself explain the pain or justify an operation. The clinical question is whether the tear is mechanically responsible for the symptoms.
Cartilage damage adds another layer. Focal cartilage defects are described by size, depth and location, and each of those affects whether a repair technique is feasible, whether a biological approach might work, and how long recovery would take. A scan report that says cartilage damage without stating these details is not enough to plan anything.
Ligament involvement complicates the picture further still. A knee with an unstable anterior cruciate ligament behaves differently from a stable knee with a meniscal tear, and the treatment priorities change accordingly. If a clinic discusses only the meniscus while your knee gives way on stairs, the assessment is incomplete.
What the imaging should tell you
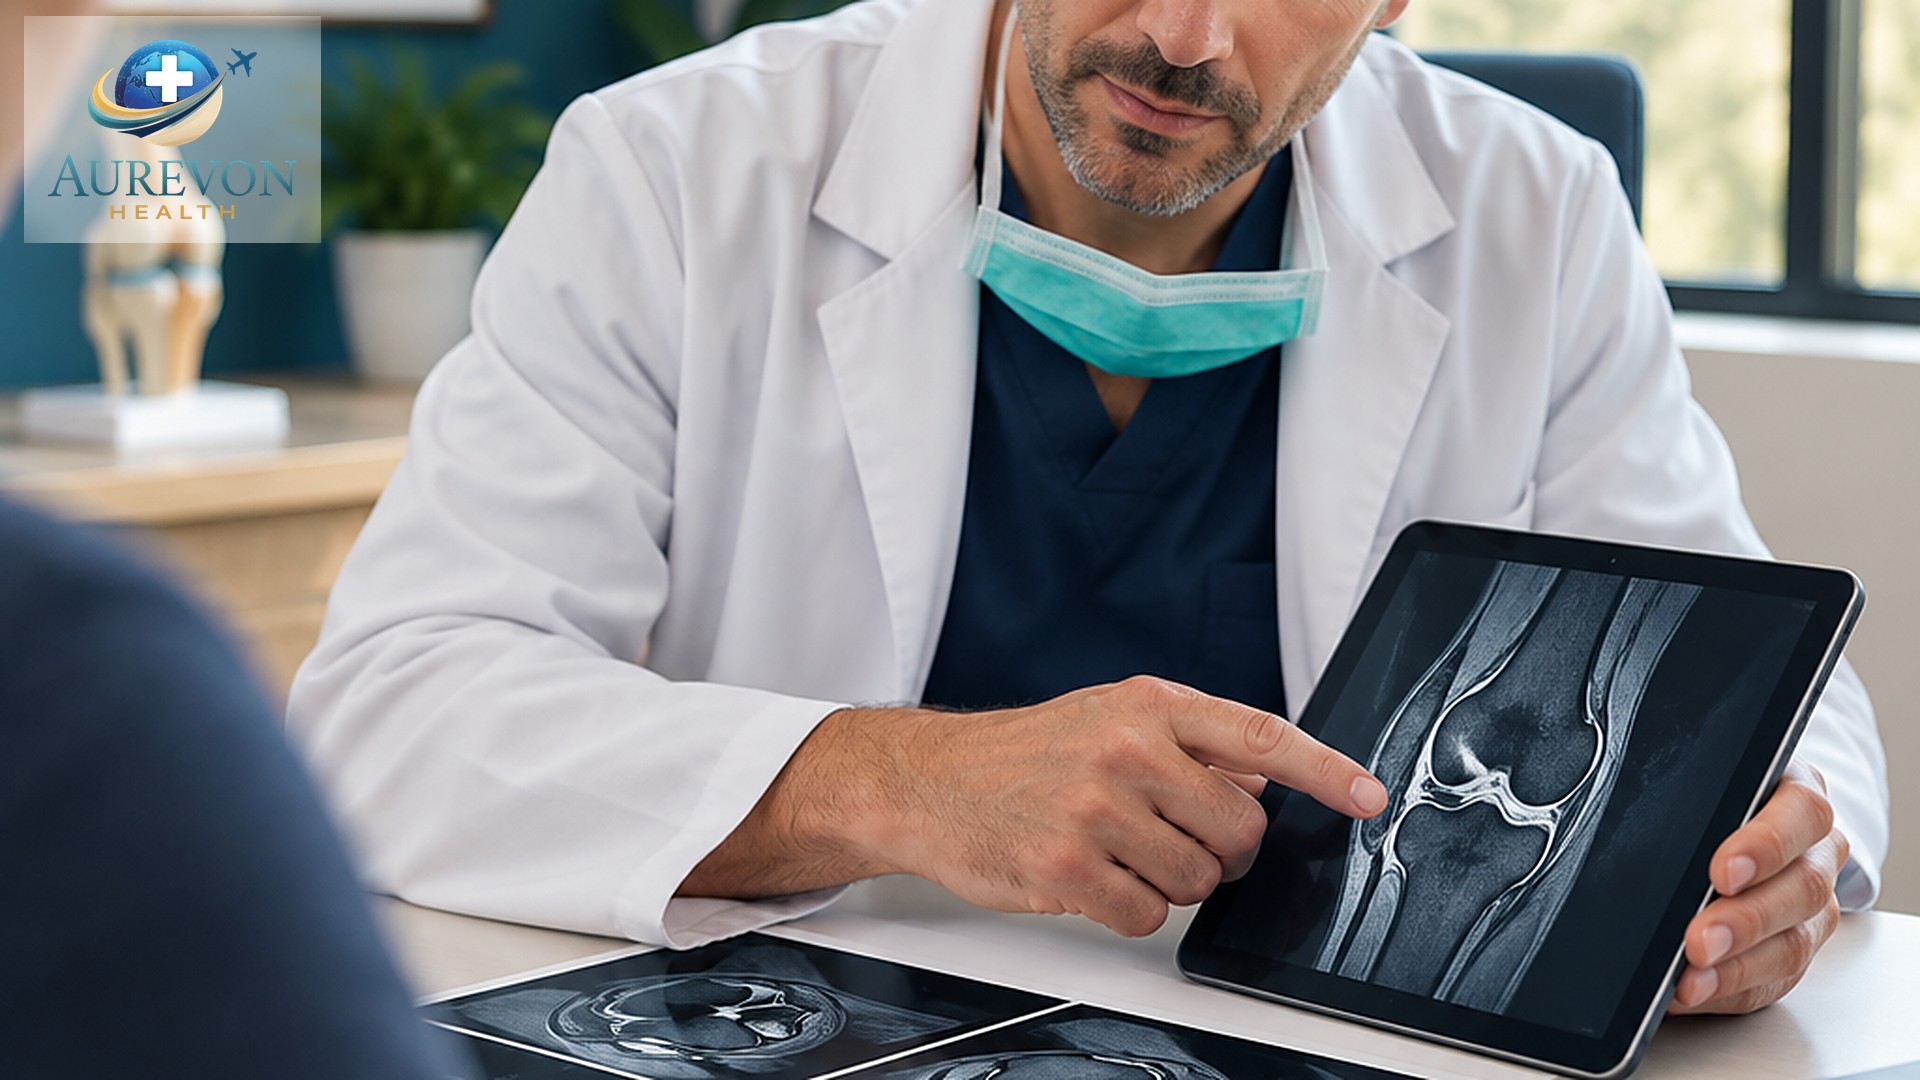
Magnetic resonance imaging is the standard investigation and, done well, it is excellent. It becomes less useful when the images are old, taken on a low field scanner, or read without the clinical history. Ask for the original DICOM files rather than photographs or a short report summary, because a surgeon planning a repair needs to see the images and not just a radiologist's sentence about them.
Some situations call for repeat imaging. If your scan is more than six to twelve months old, if your symptoms have changed, or if the scan was taken before a further injury, the pictures may no longer describe the knee you have. Many clinics will want their own views before confirming a plan, and that is reasonable.
Weight bearing radiographs matter as well, because they show joint space narrowing that indicates established arthritis. This is not a detail. A knee with significant arthritic change and a meniscal tear is a different treatment problem from a healthy knee with a tear, and the presence of arthritis changes what a sensible plan looks like.
Meniscus repair versus removal
The single most consequential question in meniscal surgery is whether the torn tissue can be repaired or whether it will be removed, and the answer depends on where the tear sits. The outer third of the meniscus has a blood supply and can heal; the inner portion has almost none. A tear in the vascular zone in a younger patient is a candidate for repair. A degenerate tear in the avascular zone of a fifty five year old is usually not.
Removal, or partial meniscectomy, relieves symptoms quickly and is technically straightforward. It also removes load bearing tissue permanently, and the literature has long associated larger resections with faster progression of arthritic change. That does not make meniscectomy the wrong operation; for many patients it is the sensible one. It does mean the decision should be explained to you in those terms rather than presented as a minor tidy up.
Ask which is proposed, on what anatomical grounds, and what the alternative would involve. Ask how much tissue would be removed if removal is chosen, expressed in approximate percentage terms. A surgeon who can answer that precisely has looked at your images properly.
Cartilage procedures and what they demand
Cartilage surgery covers a spectrum. At the simpler end, microfracture creates small channels in the bone to encourage a fibrous repair tissue to form. In the middle sit techniques that transfer or grow cartilage, and at the complex end sit procedures involving cultured cells or osteochondral grafts. Each has a different recovery profile and a different evidence base.
The critical thing for a travelling patient is that these procedures are not interchangeable, and the more demanding ones require committed rehabilitation over months. A cartilage repair that is technically successful can fail functionally if the rehabilitation is inadequate or if the patient returns to impact sport too early. That makes the rehab plan as important as the operation, and it makes the location of your rehab a genuine planning question.
Ask how many of the specific procedure the surgeon performs each year, what the published outcomes are for that technique in that age group, and what proportion of patients return to their previous level of sport. Then ask what the plan is if the procedure fails, because some of these operations have a defined revision pathway and you should know what it looks like before you commit.
The assessment a serious clinic will insist on
Meniscal and cartilage surgery is not an emergency, which means the assessment should be unhurried. A thorough evaluation includes a detailed history of the injury mechanism, a proper examination with specific provocation tests, review of the imaging in detail, and a conversation about what you want your knee to do afterwards.
- How the injury happened, and what the knee has done since
- Locking, catching or giving way, and how often
- Swelling patterns after activity
- Examination findings, including ligament stability testing
- Imaging reviewed by the operating surgeon, not only reported
- Alignment and weight bearing status
- Your age, activity level and sport specific goals
- Previous knee surgery and its outcome
- What conservative management has already been tried
If none of that list appears in your consultation, you are being offered a procedure rather than an assessment. Ask for the missing pieces before deciding.
Recovery expectations by procedure
Recovery varies more across knee procedures than patients expect. Partial meniscectomy is usually followed by rapid improvement, with walking within days and a return to desk work in a week or two for many people. Meniscal repair requires a period of protected weight bearing and restricted flexion, with return to sport measured in months rather than weeks. Cartilage procedures are slower still, with a structured progression and a long delay before impact activity.
Ask for the milestones, not the endpoint. A clinic that says six weeks without describing what should be true at two weeks, at six weeks and at three months has given you a number rather than a plan. Milestones also give you something objective to check against and something to raise early if progress stalls.
The travel plan should be built around the recovery shape rather than the reverse. Flying soon after knee surgery carries a clot risk that clinicians take seriously, and a repair with restricted weight bearing makes an economy seat and a long airport walk a poor combination. Ask when it is safe to fly, what precautions to take, and whether the clinic will provide documentation for airline and insurance purposes.
Questions that separate clinics
Some questions are so specific that the answer immediately reveals how the clinic works. Ask what percentage of meniscal tears the surgeon repairs rather than removes. A very low repair rate in a surgeon who sees many young active patients is a pattern worth understanding. Ask what technique is used for a root tear, which is a distinct and technically demanding injury. Ask whether the surgeon would operate on a degenerate tear in a patient with established arthritis, and if so under what conditions.
These are not traps. They are the questions a well informed patient asks, and clinicians generally enjoy answering them. The clinic that responds with specifics, and with the reasoning behind its preferences, is demonstrating exactly the judgement you are paying for.
Equally revealing is how a clinic responds when you ask whether surgery is needed at all. A knee with a stable tear and manageable symptoms can often be managed with targeted physiotherapy, load management and time. A clinic that acknowledges this, and explains why surgery is nonetheless the better route for you, is more trustworthy than one that treats the question as naive.
Sport, age and honest expectations
Return to sport is the outcome most patients care about and the one most often discussed loosely. The honest version distinguishes between returning to any sport, returning to the same sport, and returning to the same level. Those are three different outcomes with three different probabilities, and the difference depends on the procedure, the tissue quality and the rehabilitation.
Age is relevant but not decisive. A well motivated patient in their fifties with a repairable tear can do well with repair. A younger patient with poor rehab adherence and early return to impact can fail a good operation. Ask what the clinic's own experience suggests for someone with your profile, and ask whether it collects outcome data at all. A clinic that measures its results is more likely to describe them accurately.
Finally, be clear with yourself about what happens if you cannot return to your previous level. Some patients need a plan B, whether that is a different sport, a different role in a team, or acceptance of a knee that is comfortable for daily life but not for competitive load. Discussing that before surgery is not pessimism; it is the kind of preparation that makes the decision robust.
Frequently Asked Questions
Do all meniscal tears need surgery?
No. Many tears, particularly degenerative tears in older patients, settle with physiotherapy and activity modification. Surgery is generally considered when there are mechanical symptoms such as locking or catching, when conservative treatment has not worked, or when the tear pattern suggests repair is worthwhile in a younger knee.
How long after meniscus repair can I fly home?
Most surgeons advise waiting at least one to two weeks after knee surgery before a longer flight, and longer after a repair with restricted weight bearing. Clot risk and mobility are both factors. Ask your surgeon for a specific recommendation and request written documentation for the airline and your insurer.
Can a cartilage defect be treated without surgery?
Small defects sometimes cause manageable symptoms with strengthening, load management and time. Larger or symptomatic defects, especially in younger active patients, are more often offered surgical treatment. The decision depends on size, depth, location, alignment and your activity goals rather than on the scan alone.
What is the difference between meniscectomy and meniscus repair?
Meniscectomy removes the torn portion of the meniscus and relieves symptoms quickly, but reduces load bearing tissue permanently. Repair preserves the meniscus by stitching the tear, requires a longer protected recovery and only works when the tear is in a zone with adequate blood supply.
Should I get a second opinion before knee surgery abroad?
A second opinion is sensible whenever the recommendation involves removing tissue, drilling bone or repairing cartilage, because these decisions shape the knee for decades. Ask the second clinician what would change their mind, and compare how each one explains the reasoning rather than only the conclusion.
How much does meniscus or cartilage surgery abroad cost?
Figures vary by country, facility and technique, and the more complex cartilage procedures cost substantially more than a partial meniscectomy. Compare itemised quotes that name the procedure and include rehabilitation, rather than headline prices, and add travel and local follow up to any figure you are given.
The information provided in this article is for general informational purposes only and does not constitute medical advice. Aurevon Health is a medical tourism concierge service and is not a medical provider. We do not diagnose, treat, or recommend specific medical procedures or treatments for individuals. Always consult a qualified medical professional before making any decisions about your health or healthcare. Individual outcomes vary and cannot be guaranteed. Aurevon Health does not endorse or guarantee the services of any specific clinic, hospital, or healthcare provider.